
AI-Enabled CPAP Comfort Tools: What Sleep Apnea Patients Should Know
AI CPAP comfort tools may help personalize comfort support and early therapy coaching, but they do not replace sleep apnea testing, prescribed settings, or clinician follow-up.

AI CPAP comfort tools may help personalize comfort support and early therapy coaching, but they do not replace sleep apnea testing, prescribed settings, or clinician follow-up.
As of Friday, August 7, 2026, wildfire season remains an active Canada health topic. This article explains how to prepare for smoke events, cleaner indoor air, and where pulse oximeter spot checks fit and where they do not.

CPAP nasal congestion can make sleep apnea therapy harder, but it does not always mean CPAP has failed. Learn what nasal symptoms mean, what to check, and when to ask a clinician for help.
As of August 6, 2026, AQHI and wildfire-season alerts remain a practical Canada health topic. This article explains what moderate air-quality risk means and where pulse oximeter checks fit and where they do not.

CPAP mask leaks and dry mouth can make sleep apnea therapy harder to use. Here are the first setup, humidity, cleaning, and follow-up checks to review before giving up on treatment.

Morning headaches can occur with obstructive sleep apnea, especially alongside snoring, gasping, unrefreshing sleep, or daytime sleepiness. Learn why the symptom is a clue—not a diagnosis—and when to ask about sleep testing.
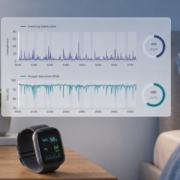
AHI counts scored breathing events per hour, while oxygen desaturation index counts oxygen-drop events per hour. Learn how both numbers fit into sleep apnea reports and overnight SpO2 trend monitoring.

Overnight oxygen saturation trends can show patterns worth discussing with a clinician, but they do not diagnose sleep apnea on their own.

A home sleep apnea test can miss some cases of obstructive sleep apnea. Here is when an in-lab study may be the better next step and how overnight oxygen trends fit into follow-up.

Short answer: Feeling sleepy after starting continuous positive airway pressure (CPAP) does not automatically mean that CPAP has failed. A clinician may first check whether the device is used during all sleep, whether mask leaks or pressure problems are allowing breathing events to continue, and whether another cause—such as insufficient sleep, medication effects, depression, or a different sleep disorder—is contributing. Persistent sleepiness deserves follow-up, especially when it affects driving, work, or daily safety.
Residual excessive daytime sleepiness is ongoing difficulty staying alert during the day after obstructive sleep apnea (OSA) treatment has begun and the airway problem appears to be controlled. It is a symptom, not a diagnosis by itself. The American Academy of Sleep Medicine states that sleepiness is clinically important because it can affect health, performance, and safety, and should be identified and addressed.
CPAP uses mild air pressure to keep the upper airway open during sleep. The National Heart, Lung, and Blood Institute (NHLBI) notes that many people experience better sleep quality and less daytime sleepiness with CPAP. Still, response is not identical for everyone, and improvement may depend on consistent use and an effective setup.
OSA-related breathing interruptions can return whenever CPAP is not worn. SleepApnea.org recommends using CPAP during every period of sleep, including naps. A 2025 meta-analysis of CPAP-treated patients also found that lower CPAP adherence was associated with residual excessive sleepiness. A device-reported “good night” should therefore be interpreted alongside how many hours the mask was actually worn and whether sleep continued after it was removed.
CPAP machines can track usage, breathing events, and mask leaks. Ongoing snoring or daytime tiredness may be a reason to ask whether the mask fit or pressure settings need review. The NHLBI advises working with a healthcare provider on mask comfort, humidification, and pressure adjustments rather than changing prescribed settings without guidance.
CPAP treats sleep-related airway obstruction; it cannot replace adequate sleep. A clinician evaluating persistent sleepiness may ask about bedtime, wake time, awakenings, shift work, alcohol, caffeine, pain, and other factors that fragment or shorten sleep. This distinction matters because “tired,” “fatigued,” and “sleepy” can describe different experiences.
Research guidance on residual sleepiness recommends looking for other possible causes before labeling symptoms as residual sleepiness from OSA. Depending on the individual, a healthcare professional may review medications, mood symptoms, restless legs, circadian rhythm problems, narcolepsy, or other medical conditions. A 2025 meta-analysis found associations between residual sleepiness and factors including more severe baseline sleepiness, depressive symptoms, and lower CPAP adherence, but these associations do not determine the cause in any one person.
Bring a simple record of symptoms and treatment use. Useful questions and data may include:
The NHLBI recommends regular checkups to confirm that sleep apnea treatment is working. A provider may review PAP data, address equipment issues, or decide whether repeat sleep testing is appropriate—for example, after a substantial weight change or when symptoms persist.
Overnight oxygen saturation trends can provide additional context for a discussion with a healthcare professional, but they do not show every breathing event and cannot establish whether CPAP pressure is correct. The ToronTek-B400 is a wristband pulse oximeter / sleep apnea monitor that records overnight SpO2 trends and produces software-generated SpO2 reports. Those reports may help a user organize observations to discuss with a clinician.
The ToronTek-B400 does not diagnose sleep apnea, measure all aspects of sleep, or replace CPAP machine data, a home sleep apnea test, laboratory polysomnography, or medical advice. Consumer oximetry readings can also be affected by motion, fit, circulation, and other factors, so isolated dips should not be self-diagnosed.
Do not drive or perform safety-sensitive work when you feel too sleepy to stay alert. The NHLBI warns that untreated sleep apnea and daytime sleepiness can impair attention and decision-making while driving. If sleepiness is sudden, severe, worsening, or accompanied by other concerning symptoms, seek prompt medical guidance.
Some people notice improvement quickly, while adjustment and symptom improvement take longer for others. Consistent use, effective mask fit, adequate sleep time, and the absence of another sleep or health problem all affect the response. Persistent symptoms should be reviewed rather than judged by a fixed deadline.
A device-reported apnea-hypopnea index can be useful, but it is only one part of treatment review. Usage hours, leaks, symptoms, the type of events reported, and clinical context also matter. Ask the treating provider to interpret the complete download if sleepiness continues.
Wake-promoting medicines are used in selected patients, and recent PubMed-indexed reviews discuss their role. They do not reopen a blocked airway or replace effective OSA treatment. Medication decisions require a sleep specialist or other qualified prescriber after treatment effectiveness and other causes of sleepiness have been assessed.
No. A wrist-worn pulse oximeter can record SpO2 trends, but it cannot determine the cause of a change or prescribe CPAP settings. CPAP adjustments should be based on clinician review of symptoms, PAP data, and testing when needed.
Disclaimer: This article is for educational and informational purposes only and is not intended as medical advice, diagnosis, or treatment. It should not replace guidance from a qualified healthcare professional. If you have symptoms, a medical condition, or concerns about your health, consult a licensed healthcare provider or seek urgent medical care when appropriate.